Perioperative care of the trauma patient requires rapid decision-making, adaptability, and a solid understanding of transfusion medicine and resuscitation principles. Familiarity with the Advanced Trauma Life Support (ATLS) algorithm is essential, particularly with respect to airway and hemodynamic priorities. In institutions designated as Level 1 trauma centers, anesthesiologists are active participants in trauma activations. Responsibilities include (1) airway management, (2) sedation for imaging and invasive procedures, and (3) assistance with high-volume blood product resuscitation. After initial stabilization in the trauma bay, ongoing care is typically transitioned to the emergency department or intensive care unit. However, anesthesiologists continue to play a vital role in the care of trauma patients beyond the initial resuscitation. In the operating room and ICU, they frequently manage patients undergoing procedures such as subdural hematoma evacuations, burn debridements, orthopedic fracture repairs, and exploratory laparotomies for intra-abdominal bleeding. These cases often require careful hemodynamic management, ongoing resuscitation, and vigilant attention to evolving clinical needs. Use your trauma rotation to build a foundation in (1) burn physiology, (2) trauma-induced coagulopathy, (3) substance intoxication, and (4) traumatic brain injury. Trauma activations require seamless coordination between anesthesiologists, emergency medicine, and surgical teams. Although the emergency medicine attending or trauma surgeon typically runs the resuscitation, your job is to: Not every trauma is a massive resuscitation, but any can escalate. Be situationally aware. As a trainee, you may not always “get to” perform the high-value procedures. Instead: Indications for trauma bay intubation include: Trauma intubations should be taken into consideration: After intubation, place a gastric tube unless there’s concern for disrupted anatomy (e.g., basal skull fracture). Trauma is a good time to become familiar with massive transfusion devices like the Level 1 or Belmont. Rehearse the setup in advance so you’re prepared when seconds matter. Preventing hypothermia is a critical priority in trauma care. All fluids should be warmed, warming blankets should be applied early, and the ambient room temperature should be increased when possible. Throughout the case, the patient should remain covered as much as feasible to minimize heat loss. Trauma patients frequently undergo damage control laparotomy as an initial intervention. Following this, they are typically transferred to the ICU for rewarming, correction of metabolic acidosis, and reversal of coagulopathy. Once stabilized, they return to the OR for definitive surgical repair. For transfusion, apply the principles discussed in the hemorrhage sections above. Use a 1:1:1 ratio of PRBCs, plasma, and platelets to approximate whole blood. Check ABGs frequently to monitor hyperkalemia. Supplement calcium after every 4 units of blood. Avoid large volumes of crystalloid; hypotension should be treated with blood, not fluid. Pressors should be minimized and never used to mask ongoing hemorrhage. Burn mortality correlates closely with the total body surface area (TBSA) affected. Severe burns trigger a robust systemic inflammatory response characterized by increased capillary permeability, widespread capillary leak, and profound local vasodilation. This cascade leads to burn shock, a distributive and hypovolemic state that the body attempts to compensate for with a catecholamine-driven surge in cardiac output. Burn patients require aggressive early resuscitation. Use the Parkland formula. For a 70 kg patient with 50% burns, for example, this would equate to 14,000 mL (14 L) total over 24 hours:
Chapter 32
Trauma
The Role of the Anesthesiologist
Team Dynamics and Situational Awareness
Airway Considerations
Temperature and Transfusion Management
Burns
Fluid Resuscitation
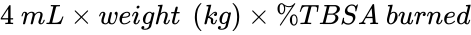
Related posts:



Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


