Obstructive sleep apnea (OSA) and obesity hypoventilation syndrome are addressed in Part 2 of this text. This section focuses on chronic obstructive pulmonary disease (COPD) and the nuances of respiratory monitoring in the perioperative period. Patients with COPD present several perioperative challenges, including an increased risk for bronchospasm, air-trapping, and delayed return to spontaneous ventilation. However, it’s important not to overstate the anesthetic risk. In reality, the greater threat comes from the nature of surgery and postsurgical factors, not the anesthetic itself. Most modern anesthetics, particularly for noninvasive procedures like imaging, endoscopy, and biopsies, have a relatively modest impact, even in advanced COPD. In contrast, major surgeries, especially those involving the chest or abdomen, carry significantly higher risk due to postoperative factors: splinting, atelectasis, impaired secretion clearance, and increased risk for pneumonia. Orthopedic surgeries can pose similar risks due to immobility in the postoperative period. Optimal anesthetic management includes: As anesthesiologists, we can become overly reliant on capnography and pulse oximetry and lose sight of their limitations. It’s important to periodically revisit what these monitors are actually telling us: This disconnect becomes especially dangerous in hypoventilating patients. The alveolar gas equation demonstrates that elevated PaCO2 can be masked by even modest supplemental oxygen, such as a few liters via nasal cannula. This can allow SpO2 to remain in the 90s while PaCO2 climbs to dangerous levels, delaying recognition of critical hypercarbia and impending respiratory failure.
Chapter 34
Respiratory Diseases
COPD and Anesthesia
Pitfalls of Respiratory Monitoring
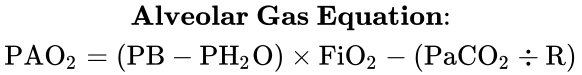
Related posts:



Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


