A strategy of time separation between the administration of a dissociative induction agent and the neuromuscular blocker to allow preintubation optimization.
INTRODUCTION
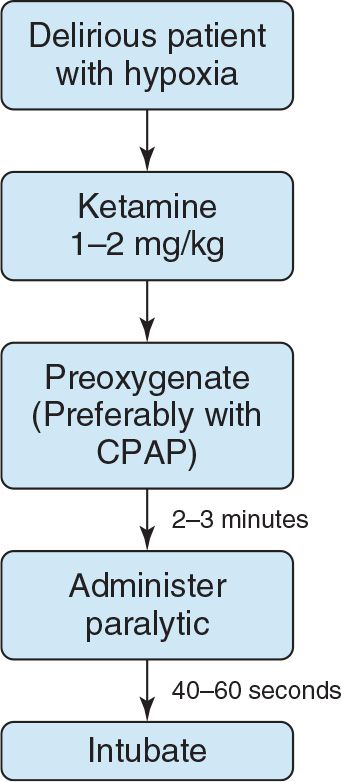
Delayed sequence intubation (DSI) differs from rapid sequence intubation (RSI), in that it separates the induction and paralysis to allow preintubation procedures such as preoxygenation in patients who are noncompliant (e.g. delirious) (FIGURE 3.1). It can be thought of as procedural sedation where the procedure is preoxygenation. In indicated situations requiring further preoxygenation, DSI is an alternative to precipitous intubation without full paralytic effect or bag-mask ventilation in the sedated and paralyzed patient. Respectively, these two traditional options increase the risk of first-pass failure or the risk of gastric insufflation and passive regurgitation in sick, nonfasted patients. Both options ensure an abbreviated period before critical levels of hypoxemia.
CLASSIC INDICATIONS
 Preoxygenation prior to intubation in a delirious or otherwise uncooperative hypoxemic and/or hypercapnic patient
 Adequate oxygenation but need for further denitrogenation of the lungs and bloodstream in order to prolong the safe apnea period in a delirious or otherwise uncooperative patient
EXTENDED INDICATIONS
 Need for an additional procedure or further optimization of physiologic parameters prior to intubation in a delirious or otherwise uncooperative patient
 Nasogastric tube placement for a patient with upper gastrointestinal bleed and stomach filled with blood
 Need to optimize patient’s blood pressure secondary to hypotension
 Need to optimize patient’s respiratory and metabolic status secondary to metabolic acidosis
CONTRAINDICATIONS
 Need for a “crash” airway
 Patient unable to breathe spontaneously
 Patient unable to protect his/her own airway
 Relative contraindications—situations in which ketamine would be less than favorable and absence of alternative agents e.g.dexmedetomidate or droperidol
 Elderly patients with coronary artery disease
 Patients with elevated blood pressure or tachycardia
EQUIPMENT
 Equipment for preoxygenation
 Nasal cannula (NC)
 Nonrebreather (NRB) mask
 Consider methods for positive-pressure ventilation if the patient is exhibiting physiologic shunt
 Ventilator and noninvasive ventilation (NIV) mask
 Bag-valve mask (BVM) with adjustable positive end-expiratory pressure (PEEP) valve
 Induction medication that maintains ventilatory drive and airway reflexes
 That is ketamine (1–2 mg/kg) given over approximately 30 seconds
 Standard equipment and medications for airway management
STANDARD TECHNIQUE
 Administration of induction agents that do not blunt spontaneous ventilations or airway reflexes
 Give a dissociative dose of ketamine (1–2 mg/kg) over approximately 30 seconds
 Alternative agents
 Dexmedetomidine 1 μg/kg over 10 minutes
 Droperidol 5 to 10 mg
 After intubation, check electrocardiogram (ECG) to determine whether any QT prolongation
 For these two latter agents, a separate induction agent should be administered just prior to neuromuscular blocker administration
 Preoxygenation and denitrogenation in standard manner with oxygen saturation >95% for 2 to 3 minutes or at least eight vital capacity (VC) breaths (note: patients who have received a DSI agent cannot take VC breaths)
 NRB
 Alternatives in patient exhibiting shunt physiology (saturation not improving with increased FIO2)
 BVM with PEEP valve
 NIV—PEEP/Continuous positive airway pressure (CPAP)
 PEEP levels between 5 and 15 cm H2O
 Follow with apneic oxygenation
 Concurrent preparation for definitive airway management in standard manner
EXAMPLE OF PROCEDURE
 Delirious hypoxic patient not tolerating an NRB for preoxygenation
 Ketamine 1 to 2 mg/kg by slow intravenous push
 Preoxygenation and denitrogenation with NRB/NC or NIPPV (Non-Invasive Positive Pressure Ventilation) for 2 to 3 minutes
 Administer NMB (Neuromuscular blockade)
 45 to 60 seconds of apnea with apneic oxygenation
 Intubate
COMPLICATIONS
Complications from DSI are no different from complications inherent in attempts to intubate hypoxic/hypercapnic, delirious and/or otherwise unstable patients, with the exception being the establishment of a prolonged safe apnea period:
 Aspiration
 Gastric distention
 Emesis with ketamine—occurs after emergence and is a concern if the patient is allowed to emerge from the dissociated state prior to endotracheal intubation
SAFETY/QUALITY TIPS
 Procedural
 Administering ketamine as a quick bolus will often cause 15 to 30 seconds of apnea; this can be avoided by pushing ketamine more slowly (over 30 seconds)
 Application of a NC at high flow, in addition to either a face mask or NIV oxygenation, will optimize oxygenation and facilitate apneic oxygenation after the paralytic is given
 Avoid very high positive pressure (>15 cm H20) when using NIV
 Cognitive
 The intubating provider should be at bedside during the entire DSI procedure, prepared to abort DSI at any point and commence with RSI (by giving the paralytic)
 Although the goal of DSI is to optimize intubating conditions, in some cases, the underlying insult can be adequately addressed during the dissociated period, and intubation avoided. We recommend that a full intubation setup be prepared for every DSI case, however.
 Current alternatives to ketamine are inferior to ketamine for facilitating DSI; be cautious if using any other agent
Related posts:



Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


